

Our biweekly State of U.S. Vaccine Policy, published in partnership with CIDRAP (the Center for Infectious Disease Research and Policy at the University of Minnesota), is pausing this week and will pick back up next week. We have plenty to say and a lot to catch up on.
So, today we’re doing something different.
Yesterday I had the honor of sitting on a panel hosted by Montana Families for Vaccines, a grassroots network of Montanans advocating for fact-based immunization policy. The event was part of their annual celebration of Dr. Maurice Hilleman, the Montana farm kid who went on to develop more than 40 vaccines, including the combined MMR (no big deal!). His work has likely saved more lives than that of almost any other scientist in history.
My fellow panelists were the legendary Dr. Paul Offit, Dr. Demetre Daskalakis, and Kirsten Hilleman, Dr. Hilleman’s youngest daughter. Kirsten appears in the documentary, Hilleman: A Perilous Quest to Save the World’s Children, receiving the mumps vaccine her father developed from a swab he took from her sister Jeryl Lynn’s throat in the middle of the night. (The Jeryl Lynn strain is still the mumps component in the MMR your kids get today. Isn’t that incredible?)
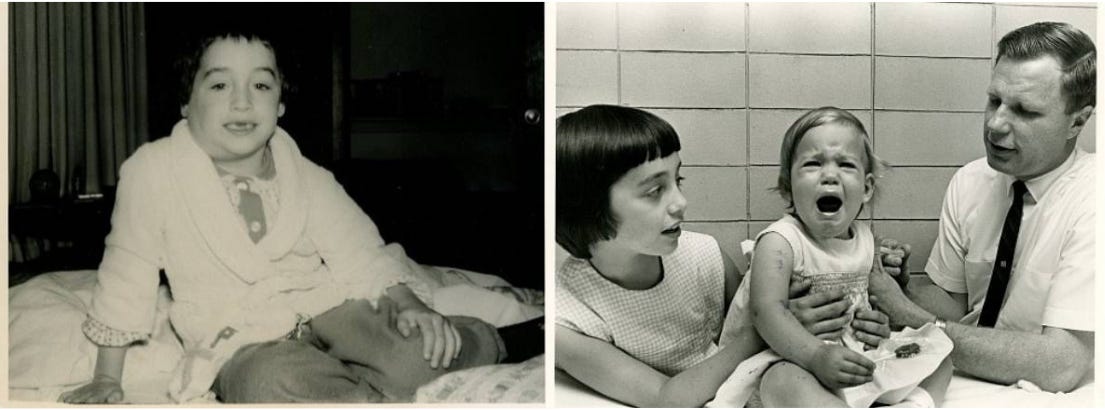
The timing of the panel was kind of eerie. We spent an hour celebrating the man who did more than anyone to make measles a memory in this country, in the same week that Pennsylvania confirmed two unvaccinated Lancaster County residents had died of it. They were the state’s first measles deaths in 35 years and the first anywhere in the country this year.
It has since become a political fight, which we posted about on our social media pages. Pennsylvania used the term “measles-associated,” which it applies when there’s laboratory or epidemiologic evidence of measles even if the coroner hasn’t assessed measles as the immediate cause, and that word has been seized on to argue nobody actually died of measles. One of the two was a newborn. The Lancaster County coroner says the baby’s primary cause of death was a laceration (a tear) of the spleen. A postmortem test on the baby’s lung tissue found evidence of a measles infection acquired before birth, a finding NBC News independently confirmed with the coroner. The autopsy did not find the spleen to be enlarged, and investigators are still determining what caused the laceration. Pennsylvania continues to classify the death as measles-associated. Almost nothing has been released publicly about the second death.
The state’s health department told CIDRAP that the spleen is full of immune cells, which makes it a place where the measles virus can survive and multiply, causing inflammation and tissue damage. The department did not specify whether that requires visible enlargement. Dr. Offit told the Inquirer that the coroner’s account doesn’t add much, since measles can cause an enlarged spleen, birth can rupture it, and once a spleen has ruptured it’s difficult to tell whether it had been enlarged beforehand. Secretary Kennedy went much further, suggesting on X that the deaths may have been fabricated altogether by one of the governor’s staffers.
The fight has spilled over into social media, where some people are telling us we are overreacting about the deaths. That is a sentiment I simply cannot grasp.
The “died with it, not from it” framing often gets treated as a gotcha. Let’s unpack what those phrases really mean. Infections often kill through the complications they cause rather than by appearing alone on a death certificate. So a death by complication is still a death from the disease, even when it’s officially classified as “associated with” the disease. For example, measles most commonly kills through pneumonia or encephalitis, where the infection sets off the cascade that ends in death. But that same principle can’t be stretched to settle every case automatically, either. A spleen injury during birth is very rare. While the measles virus can inflame and damage the spleen, the mechanism by which that might lead to a laceration isn’t well established in the medical literature. The role that measles played in these two deaths is a question the clinical and forensic evidence will have to answer, and that evidence isn’t all public yet. One thing isn’t in dispute. This baby had measles, acquired before birth, and no newborn is eligible for the MMR, which isn’t routinely given until 12 months (but can be administered as young as 6 months in an outbreak). Whatever the coroner concludes about the spleen, an infant was infected because measles is circulating in a community that no longer has enough protection to stop it.
Please remember this: what a coroner determines, what a health department classifies, and what a politician says about both are three different things. Most of the confusion right now comes from treating them as one. No matter what, it is alarming that we are seeing this number of cases of a disease that was eliminated in the United States in 2000. Plus, as Dr. Offit points out, the fact that these numbers are so high during the summer (when measles is typically a winter disease) does not bode well.
Back to the panel… The first question of the day was directed to me. I was asked to provide a summary of where things stand with vaccines today (no biggie, ha!). I walked through the high-level way my brain organizes the vaccine landscape. We often share deep dives on specific issues as they unfold, so I thought it might be helpful to step back and share the 30,000-foot view with you.
Let’s discuss…
Taking multiple hits
I sort all of this into three buckets. What’s happening federally, what’s happening in the states, and what’s happening in the broader discourse. Within each bucket, there are many separate ways vaccines can be affected, which is what makes this feel less like one fight and more like many at once.
Picture arrows hitting different parts of the body simultaneously. One is aimed at the schedule, meaning which vaccines are recommended and when. Another at access, meaning what insurance covers and whether the system actively offers you a vaccine, which can change without the schedule changing at all. Another at what officially counts as a vaccine injury, meaning which conditions get presumed to be caused by a vaccine without evidence that they are (this impacts how risky it becomes for manufacturers to produce vaccines). Another at state exemption laws. Another at who sits on the committees that write the recommendations in the first place. Another at the data systems that tell us how many kids are actually protected. That’s a lot of arrows.
Federal
The most important thing to know about the federal picture is that most of what’s been attempted is currently on hold. A brief recap…
In June 2025, Secretary Kennedy removed all 17 members of the committee that advises CDC on vaccines and replaced them with his own appointees. In January, HHS narrowed the childhood vaccine schedule to protect against 11 diseases instead of 17, with no public comment period, no advisory review, and no new safety data. In March, a federal judge in Boston blocked the bulk of it in a case brought by the American Academy of Pediatrics and six other medical and public health groups, finding the administration likely broke the law both in how it rewrote the schedule and in how it rebuilt the committee. The schedule changes, most of Kennedy’s appointments, and the votes the reconstituted committee took are all frozen. HHS has appealed.
On August 10, the President signed an executive order pursuing the same direction from a different angle. It endorses the shorter list, calls for splitting the MMR into three separate shots, directs that vaccines be given at separate visits, and points the Justice Department at state exemption laws.
The MMR provision lands at a particularly bad moment given where measles is right now. No standalone measles, mumps, or rubella shots are licensed in the United States, and both Merck and GSK have said they aren’t interested in making them. There’s no evidence that separating the shot helps anyone, and doing it would mean more needles, more visits, and more chances for a child to miss a dose.
There’s also a push to add autism to the federal vaccine injury table. If a listed injury occurs after a listed vaccine within a specified time window, the program generally presumes the vaccine caused it rather than requiring the claimant to prove causation. Adding autism would create a legal presumption of causation for something decades of research say vaccines don’t cause. With roughly 120,000 children diagnosed with autism in the U.S. each year, even a fraction becoming eligible for presumptive claims could create enormous financial exposure for the program and vaccine manufacturers, potentially making some vaccines too risky to manufacture.
How vaccines get categorized, and why that affects access
We haven’t discussed this yet, so we’ll take a bit longer to explain. On August 21, HHS announced a public comment period on a request for information about how vaccine recommendations get labeled.
Federal recommendations currently fall into three categories. Routine means nearly everyone in an age group should get the vaccine; MMR for children is an example. Risk-based is narrower, for people with a particular health condition, job, exposure, or travel plan; yellow fever vaccination before travel to certain countries is one example. Shared clinical decision-making covers cases where a vaccine may make sense for some people in a group but not everyone; HPV vaccination for adults ages 27 to 45 is an example.
The request asks whether those three categories are enough, floating labels like recommended “with qualification” and recommended “but not during infancy” without defining them or naming a single vaccine that might move.
It changes nothing by itself, but the category a vaccine falls into has big implications. It’s tied to coverage protections, including requirements that many health plans cover recommended vaccines without cost sharing, and some legal experts have warned that new categories could open a path for insurers to drop that and could affect Vaccines for Children eligibility. It also shapes what pops up automatically in a clinic’s system and whether the pediatrician or family physician raises a vaccine as a given or as an option. HHS wouldn’t need to take a vaccine off the schedule to sharply cut how many kids get it. Changing the category would do that.
Some of what the request raises is legitimate. Recommendations should be easier to understand, and agencies should be clearer about uncertainty. The concern is what happens if things other than evidence start deciding what counts as medically recommended.
If you want to comment, our friends at Voices for Vaccines have organized a webinar to help draft one! It will take place on Tuesday, September 2nd at noon EST. Register here! If you are unable to attend, here are some ideas to get you started:
Timing should follow risk. Babies are vaccinated early because they’re the ones most likely to be hospitalized or die from these diseases, so a category like “recommended, but not during infancy” makes being a baby the reason to wait.
All strong evidence should count, not just randomized trials. Once we know a vaccine prevents a serious disease, leaving a group unprotected for comparison is unethical, which is why we also rely on health databases, real-world studies, and safety monitoring.
Shared decision-making is for real uncertainty. If a vaccine clearly helps nearly everyone in a group, it should stay routine.
Vaccines given together should stay together when the studies support it. Separating them means more appointments, more needles, and longer stretches when kids aren’t protected.
Science questions and policy questions are different questions. Whether a vaccine prevents disease is about evidence. How recommendations interact with consent and exemptions is for policymakers.
Submit through Regulations.gov by searching Docket No. HHS-OS-2026-0332. Comments are posted publicly, so don’t include anything you wouldn’t want online. Comments are due by September 20, 2026.
States
With the federal changes stuck in court, a lot of the action has moved to statehouses and state health departments, where the federal injunction doesn’t apply. It’s moving hard in both directions at once. (We cover a lot of this in our biweekly series with CIDRAP. Stay tuned for that next week.)
Florida is the clearest example on one side. On August 20, the state surgeon general approved a proposed rule that would:
Remove hepatitis B, chickenpox, Hib, and pneumococcal vaccines from school and childcare entry requirements.
Change the religious exemption form to accept any moral or ethical objection.
Let parents and college students opt out of the state immunization registry.
The rule is open for comment through September 14 and isn’t final.
That third one is the arrow aimed at the data. A registry is one of the main ways a state knows who’s been vaccinated. Schools use it to verify status, it’s where coverage numbers come from, and it’s the first thing a health department pulls up when measles shows up at an elementary school and someone has to figure out fast which kids are vulnerable. Let enough families opt out and you’re managing an outbreak with a much less complete picture of who’s protected.
Going the other way, California has said it will keep its school requirements regardless of the executive order, and it’s far from alone. A majority of states have said they’ll look somewhere other than CDC for at least some childhood vaccine recommendations, many to the American Academy of Pediatrics or their own expert panels, specifically to protect their policies from federal changes.
So, the schedule a family actually encounters is becoming a function of their zip code.
New CDC data for the 2025-26 school year show exemptions rising in 41 states and D.C., the biggest annual jump in more than a decade. Coverage fell for every reported vaccine, leaving roughly 280,000 kindergartners without a documented MMR series. In Lancaster County, where the two deaths happened, MMR coverage is 87.6%, well below the roughly 95% generally needed to keep measles from spreading.
Parting thoughts
And then there’s the public discourse around all of this. Vaccine myths and misconceptions are everywhere, increasingly amplified by prominent health officials alongside the usual social media chatter. As policy changes play out publicly and often confusingly, that constant noise makes it harder to know what to trust, and steadily erodes trust itself. Perhaps that is the point?
The moderator of the panel closed by asking each of us for a final thought.
Dr. Daskalakis reminded us to vote with our feet. Where we get our care, where we spend our money, which institutions we support, who we elect. Public health isn’t only something that happens to us from Washington. It’s also the accumulated weight of a lot of individual choices, and those choices are still ours. He also said we need to build bridges, not dams. Most of the people who are uncertain about vaccines aren’t the loud accounts online. They’re quieter, and reaching them means being willing to cross over and talk with them, or at least meet them partway.
Dr. Offit went to Galileo. After the Church forced him to recant the idea that the Earth moves around the sun, Galileo is said to have muttered “eppur si muove.” And yet it moves. The science doesn’t care what we do to it or say about it. People can spread lies, agencies can be reorganized, labels can be rewritten. Measles will still be one of the most contagious viruses on earth. The MMR will still work. The Earth will still go around the sun.
Here’s where I landed. Conditions right now are close to ideal for distrust of vaccines to take hold. There’s real frustration out there, people are tired, and the pandemic left behind divisions that never closed. That frustration is legitimate, and it’s also easy to harvest.
But we're not without options while all of this plays out. Policy matters enormously, which is why we cover it every other week and why we're telling you how to comment on that federal docket. It also isn't the only place any of us has leverage. Some of the most consequential conversations about vaccines happen in kitchens and group chats and school pickup lines, with people who already trust us. That trust doesn't scale, which is exactly why it works.
Nobody changes their mind because of a viral post. People change their minds because someone they love sat with them and took the question seriously.
Those conversations can be uncomfortable. Please have them anyway.
Stay Curious,
Unbiased Science

In my conversations I add that the MMR shot cost is for 1 visit... while separating the shots incurs paying for 3 visits. There's the health cost and the financial cost.
My family has ties close to the Lancaster Mennonite community. We're all vaccinated, except my toddler has only had the first shot. I worry that with herd immunity down and grandparents who might be exposed through interactions, it could spread to her. But I don't know if I should ask her doctor for an early second dose or if it's better to wait. It's really scary, not to mention heartbreaking and a needless tragedy.
What a high this article started off with though. I'll definitely be watching the movie about the incredible Dr. Hillemon. Thank you for your work.